
Prolactinoma Explained: Symptoms, Tests and Treatment Options
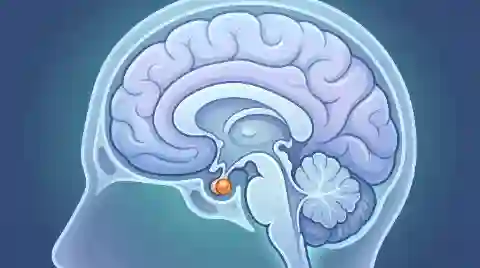
A prolactinoma is a non-cancerous (benign) tumor of the pituitary gland that produces the hormone prolactin. It is the most common type of hormone-producing pituitary tumor, and most people who are diagnosed with one can be treated successfully without surgery.
Because the tumor releases extra prolactin, the body behaves as if it were pregnant or nursing. That is why the first signs are often changes in periods, fertility, libido or unexpected milk discharge. Larger tumors can also press on nearby structures and cause headaches or changes in vision.
This article walks through who gets prolactinomas, the symptoms in women and men, the tests used to confirm one, and how treatment works from medication to surgery.
Doctors consider the condition one of the more common benign pituitary tumors, and it is seen more often in women than in men.
Microprolactinoma and Macroprolactinoma
Prolactinomas are grouped by size.
- Microprolactinoma: smaller than 10 mm (about 1 cm). These are more common in women and usually found early because periods change.
- Macroprolactinoma: 10 mm or larger. These are more often found in men, frequently later, because symptoms can be subtle until the tumor grows.
Size matters because it guides how closely the tumor is monitored and whether pressure on the optic nerves is a concern.
Common Symptoms
Symptoms linked to high prolactin
- Irregular or stopped periods
- Milk discharge from the breasts when not pregnant or breastfeeding
- Difficulty becoming pregnant
- Reduced sex drive, and in men, erection problems
- Breast tissue growth in men
Symptoms linked to tumor size
- Persistent headaches
- Reduced side (peripheral) vision or blurred vision
- Fatigue and, occasionally, nausea
If you notice vision changes together with headaches, seek medical attention promptly.
What Causes a Prolactinoma?
In most people the cause is unknown. A small number of cases are linked to inherited conditions such as multiple endocrine neoplasia type 1 (MEN 1). They are not caused by lifestyle habits, and a prolactinoma is not a sign of cancer.
It is also important to know that other things can raise prolactin without any tumor, including some medicines and an underactive thyroid. Our guide to the high prolactin levels explains these differences in more depth.
How Is a Prolactinoma Diagnosed?
- Prolactin blood test. A clearly raised level, often repeated to confirm, is the first clue.
- Thyroid and other hormone tests. These rule out causes that can mimic a prolactinoma and check whether other pituitary hormones are affected.
- Pituitary MRI. Imaging shows the tumor and measures its size.
- Vision testing. This is recommended when the tumor is large or near the optic nerves.
Treatment Options
Not every prolactinoma needs treatment. A very small tumor causing no symptoms may simply be watched with periodic blood tests and scans. Treatment becomes important when there are symptoms, fertility goals, bone loss risk or a growing tumor.
Medication
Dopamine agonist medicines are the usual first choice. They lower prolactin and often shrink the tumor. Cabergoline is commonly prescribed because it is taken only once or twice a week and tends to be well tolerated; see our overview of cabergoline for prolactinoma and the broader pituitary tumors article.
Doses begin low and are adjusted according to blood tests, so the schedule should always come from your prescriber. Be aware of the side effects, such as nausea, dizziness and headache, which often settle with time. Long-term users should also read about heart valve monitoring.
Surgery
Surgery, usually through the nose (transsphenoidal), is considered when medicine does not work, cannot be tolerated or when a large tumor threatens vision.
Radiotherapy
Radiation is reserved for tumors that keep growing despite medication and surgery.
Prolactinoma, Fertility and Pregnancy
High prolactin can stop ovulation, but fertility often returns once levels are controlled. Women planning pregnancy should talk to their doctor first, because treatment is usually reviewed and monitored closely throughout pregnancy. More on this topic is in our post on infertility and prolactin.
Can Treatment Ever Be Stopped?
Some people can reduce or stop medication after several years if prolactin stays normal and scans show the tumor has shrunk or disappeared, but this decision must be made with an endocrinologist, with regular follow-up afterward. Read about what to expect in stopping cabergoline.
Frequently Asked Questions
Is a prolactinoma cancer?
No. Prolactinomas are benign tumors, and they almost never spread.
Can men get a prolactinoma?
Yes. It is less common than in women, but men are often diagnosed with larger tumors because symptoms such as low libido are easy to overlook.
Will I need surgery?
Most people respond to medication and do not need surgery.
How long does treatment take to work?
Prolactin levels often fall within weeks of starting medication, while tumor shrinkage and the return of regular periods can take several months.
How often are follow-up tests needed?
Your doctor will usually check prolactin every few months at first, then less often once levels are stable, with periodic MRI scans based on tumor size.
This article is for general education and does not replace advice from a qualified healthcare professional.

